Table of content
Table of content
Most people never think about dental nerve removal until a tooth starts to hurt in a way that is impossible to ignore. At first it might be a quick sting when you drink something cold, or a sharp twinge when hot coffee reaches a certain tooth. You hope it will pass.
Then it changes. You find yourself chewing on one side only. You keep touching your cheek. The sting becomes a deep, throbbing ache that wakes you at night, and painkillers buy a few hours before it returns.
At that stage the nerve inside the tooth is usually inflamed or infected — and it will not settle by itself. Dental nerve removal is performed through root canal treatment: the infected pulp is taken out, the inside of the tooth is cleaned and sealed, and your own tooth stays in place. The NHS puts the alternative plainly: if you have an infected tooth and do not have root canal treatment, you may need to have the tooth taken out.1
This article explains what nerve removal actually involves, what happens afterwards, and the one thing that decides more than anything else how long the treated tooth lasts — which most pages on this subject leave out entirely.
What “Nerve Removal” Actually Means
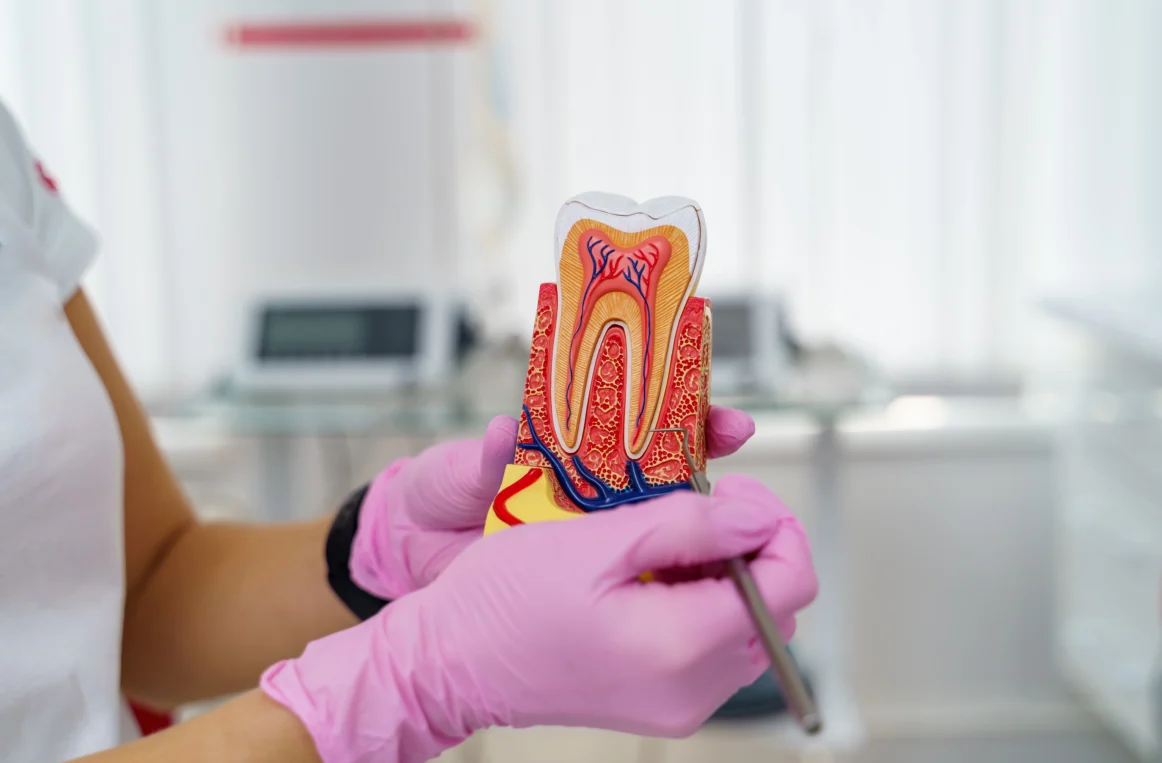
Inside every tooth is a small chamber holding soft tissue called the pulp — the nerve, blood vessels and connective tissue together. In childhood the pulp drives the tooth’s development. Once the tooth is fully formed, it no longer needs the pulp to stay in your mouth: the tooth is held and supported by the surrounding bone and periodontal tissues.
The pulp becomes vulnerable when bacteria reach it. The NHS lists the routes: tooth decay, gum disease, a tooth that is chipped, broken or cracked, and a dental abscess.1 Once bacteria are inside, infection and inflammation follow — and that is the pain that stops responding to painkillers.
An honest point about the word “dead”. After the pulp is removed the tooth is no longer vital — that is the whole purpose of the treatment. What it keeps is everything that matters day to day: your own root in your own bone, normal biting, and a tooth that looks and feels like the rest.
But it is not identical to a live tooth, and the difference is worth knowing because it explains the aftercare. Losing the pulp also means losing the pressure feedback it provided, so a root-filled tooth can take heavier loads than you realise without warning you. Root canal instrumentation also removes some dentine from inside the root. Together, these leave the tooth more prone to fracture than a vital one.2 That is not a reason to avoid the treatment — it is the reason the restoration on top is not optional, which we come back to below. If you are weighing this up against losing the tooth, our guide to whether a dead tooth can be saved covers the decision.
Root Canal Procedure: Step by Step
Before anything begins, your dentist takes radiographs to see how far the problem has reached and whether the root and surrounding bone are involved. Then:
- You are fully numb. A local anaesthetic is given first — you are awake but should not feel pain.1 Most patients describe pressure and movement rather than discomfort.
- A small access point is made through the tooth to reach the pulp chamber.
- The infected pulp is removed. Where there is an abscess, it is drained at this stage.1 This is usually when the pressure pain starts to ease.
- The canals are cleaned, disinfected and shaped so nothing is left behind for bacteria to regrow in.
- The canals are dried and sealed with biocompatible filling material, and the tooth is closed.
- The tooth is restored — with a filling, or a crown where the tooth was badly infected or heavily broken down.1
How many appointments? This is the part travelling patients most need to know, and most pages skip it. The NHS states that root canal treatment usually takes two or more appointments, each lasting one to two hours or sometimes longer, with a temporary filling in between.1 Some cases are completed in one visit and some are not — which is a question to settle in your treatment plan before you book flights, not after you arrive.
The Crown Is Not an Upsell — It Is What Makes the Tooth Last
If you take one thing from this page, take this one.
The root filling deals with the infection. The restoration on top of it decides how long the tooth survives. It does two jobs at once: it seals the treated canal system against bacteria getting back in from the mouth, and it protects a weakened tooth from splitting under normal chewing.2
The evidence on timing is striking. In a retrospective study cited in the British Dental Journal, root-filled back teeth that received a crown within four months were three times less likely to end up extracted than teeth left longer under a composite or amalgam filling.2 For back teeth with a large cavity after root canal access, some form of cuspal protection is specifically indicated to stop the cusps flexing and the tooth fracturing.2
This matters more for travelling patients than for anyone else, because the gap between “root canal done” and “crown fitted” is exactly where a trip abroad can leave a tooth sitting under a temporary restoration for months. Ask how and when the final restoration will be placed before you commit to a plan. A clinic that treats that as a detail is not planning your tooth’s next ten years.
Root Canal vs. Tooth Extraction: Why Keeping the Tooth Usually Wins
Patients often ask why they should not simply have the tooth out, since extraction looks simpler. It is simpler on the day. What follows is not:
- A gap forms, and neighbouring teeth start to drift into it
- The opposing tooth can over-erupt into the space
- The remaining teeth absorb the chewing load that tooth used to carry
- The bone in that area gradually resorbs once there is no root in it
Replacing it then means a dental implant or a bridge. Both are excellent treatments and both are more involved than keeping what you already have — more appointments, more cost, and in the case of an implant, surgery and healing time.
That is the case for root canal treatment, and it does not depend on where it is done. A well-executed root canal keeps your own root in your own bone — and nothing replaces that as well as it does. Where the tooth genuinely cannot be saved, extraction is the right call and should be said plainly.
Am I a Candidate for Root Canal Treatment?
Nerve removal is likely to be needed if you have:
- Intense or lingering sensitivity to hot or cold
- Deep pain that comes and goes, or wakes you at night
- Pain when biting or when the tooth is tapped
- Swelling around the tooth, or a pimple-like bump on the gum
- A cavity that has reached the inner layers of the tooth
- A tooth that has darkened after an old injury
Swelling of the face, or pain with fever, should be seen urgently rather than added to a travel plan — see what to do about severe toothache.
Root canal treatment may not be the right option if:
- The tooth has broken down below the level where it can be rebuilt
- There is not enough sound tooth left to hold a crown
- The supporting bone has been extensively lost
- The tooth cannot be restored to proper function
Restorability is a judgement made from the tooth and the radiograph together — how much sound structure remains, and whether a crown can get a grip on it. Where the answer is no, extraction with an implant or bridge is the honest recommendation.
What to Expect After the Treatment
Many people expect recovery to be the painful part. In practice, once the inflamed nerve is gone, the deep pressure ache that brought you in usually settles quickly.
What you can expect instead:
- Numbness in the jaw and face for several hours while the anaesthetic wears off.1
- Swelling and soreness around the tooth, particularly on biting. The NHS notes this should improve over a couple of weeks — so if the first few days are still tender, that is expected rather than a sign something is wrong.1
- Paracetamol or ibuprofen for discomfort, and care not to bump or knock the mouth.1
Alongside that: keep to soft foods for a short period, brush gently but keep cleaning the area normally, attend any follow-up appointments, and keep regular check-ups afterwards.1 Once the tooth is fully restored it should feel entirely normal — most patients forget which one it was.
Pain that increases after several days, or swelling that spreads, is worth a call rather than a wait.
Root Canal Treatment Costs: Turkey vs. Other Countries
Most people researching treatment abroad start with the price, because root canal treatment in their own country is expensive — particularly once the crown is added.
Read the following as approximate market ranges, not as a quote. What a root canal actually costs depends on which tooth it is — an incisor with one canal and a molar with four are different pieces of work — how many appointments it needs, and whether a crown or a post is part of the plan. Your own figure is confirmed in writing after an assessment.
- United States: roughly $600–$1,600 per tooth for the root canal itself
- United Kingdom (private): roughly £300–£900 — broken down here. On the NHS, root canal treatment falls under band 2.1
- Western Europe: roughly €200–€1,600
Turkey is lower, and the reason is worth being precise about: it is the local cost base — staffing, premises and laboratory work — not fewer appointments, cheaper materials or a shorter procedure. The clinical steps are the same steps described above. When you compare, compare the whole plan including the crown, because a root canal price without the restoration is not the real number in any country. The wider picture is in our guide to dental treatment prices in Turkey.
Why Many Patients Choose Turkey
Patients travel from Europe, the UK, the Middle East and further because:
- Clinics are equipped for magnification, rotary instrumentation and 3D imaging as routine endodontic practice
- Waiting times are short — treatment can usually begin within days
- The treatment plan is shared and agreed online before anyone travels
- Hotel and transport coordination is handled alongside the clinical appointments
One caution specific to this treatment, and we would rather say it than not: root canal treatment is not reliably a one-visit procedure, and the final crown is often a second stage.1 Before booking, get the number of visits and the plan for the final restoration in writing. That single question separates a plan that holds from one that leaves you at home with a temporary filling — see also how to find a dentist in Turkey and our guide to dental tourism.
Why Choose DentSpa for Your Root Canal Treatment
- PhD-level specialist dentists, with professors and associate professors planning and performing treatment.
- The restoration planned with the root canal, not after it — because the crown is what decides how long the tooth lasts, and the timing is part of the plan you agree before travelling.
- Radiographic assessment before anything is started, including whether the tooth is restorable at all.
- The number of visits agreed in advance, in writing, along with the cost.
- Complete A–Z care from your online consultation through to aftercare.
You don’t have to take our word for the standard. DentSpa was named best dental clinic in Europe in the odontology category at the European Awards in Medicine,3 is licensed by the Turkish Ministry of Health, certified to ISO 9001 and ISO 10002, and a member of the Turkish Dental Association. For treatment planned from abroad it also holds the Certification for Excellence in Medical Travel Patient Experience from Global Healthcare Accreditation.4 More than 50,000 international patients have been treated since the clinic was founded in Istanbul in 2018 — see real cases in the smile gallery and read the verified reviews.
If a tooth is hurting and you want to know whether it can be saved, book a free consultation or message us on WhatsApp. You will get an assessment of the tooth, the number of visits it needs, and a plan for the final restoration — including, where it applies, the answer that the tooth cannot be saved.
Before & After
Frequently asked questions
Is dental nerve removal the same as root canal treatment?
Does it hurt?
Is the tooth dead afterwards?
Do I really need a crown afterwards?
How many appointments does it take?
Can I just have the tooth taken out instead?
When is a tooth beyond saving?
What if the pain gets worse after treatment?
Sources
- NHS — Root canal treatment
- Patel SR, Youngson C, Jarad F. Principles guiding the restoration of the root-filled tooth. British Dental Journal, 2025. doi:10.1038/s41415-025-8401-4
- The European Awards in Medicine — DentSpa Clinic — European Award in Medicine in Odontology
- Global Healthcare Accreditation — DentSpa Strengthens Global Trust in Turkey’s Dental Services with GHA Certification
















 70%